Every brain-computer interface has to answer one question before anything else: how close does it get to the neurons? That single choice, go inside the skull or stay outside it, shapes everything else about the device, from how much it can do to how risky it is to use. It is the fault line that separates invasive BCIs from non-invasive ones, and understanding it explains most of the headlines you read.
The trade-off is blunt. Invasive interfaces place electrodes in or on the brain and get clean, detailed signal, at the cost of surgery. Non-invasive interfaces read from outside the head: safe and cheap, but working through the skull means a noisier, blurrier picture.
The trade-off in one table
| Item | Invasive | Non-invasive |
|---|---|---|
| Signal quality | High and precise | Lower, noisier |
| Risk | Requires surgery | Minimal |
| Cost | High | Low |
| Typical use | Medical restoration | Focus tools, consumer, research |
First, how any BCI reads the brain
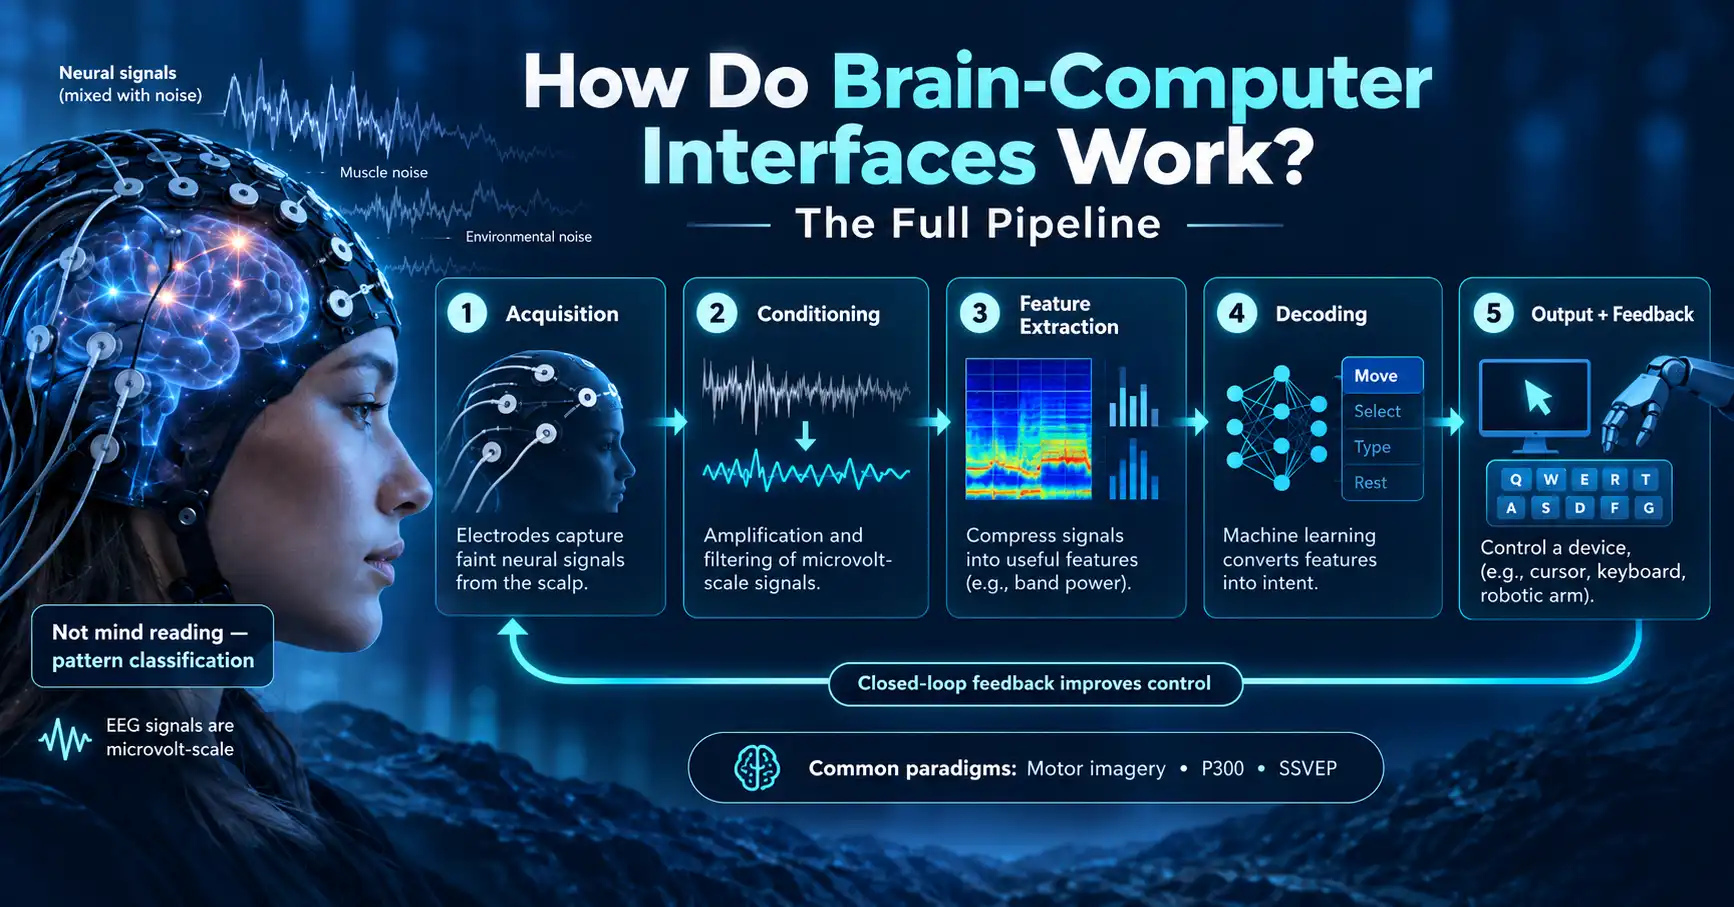
Whatever the approach, the basic idea is the same: neurons fire, that activity produces measurable electrical signals, and the device translates those signals into commands. The difference is purely one of proximity. Sit an electrode right next to a neuron and you hear it clearly; move it outside the skull and you are listening to the crowd through a wall. If you want the full picture of that translation process, our guide to how brain-computer interfaces read your thoughts covers it properly.
Invasive: fidelity at a price
Invasive BCIs, the implanted kind, place electrodes directly into the cortex or on its surface. Because they sit right at the source, they capture the activity of individual neurons or small groups with remarkable clarity. That high fidelity is what makes fine, fluid control possible, and it is why the most impressive demonstrations, restoring movement or speech to paralysed patients, use invasive devices. The price is obvious and non-trivial: it takes neurosurgery, it carries infection and tissue-response risks, and questions about how well implants hold up over many years are still being answered. For most people, that price only makes sense when the medical need is serious.
Non-invasive: safe, but listening through a wall
Non-invasive BCIs read brain activity from the outside, most commonly with EEG sensors resting on the scalp. Nothing is implanted, so there is essentially no medical risk, the hardware can be cheap, and anyone can put one on and take it off at will. That accessibility is why every consumer “brain” gadget (focus headbands, meditation trainers) uses this approach. The drawback is signal quality. The skull smears and weakens the electrical activity before it reaches the sensors, so the data is coarser and more prone to noise. You can detect broad states and simple intentions; you cannot yet get the crisp, neuron-level detail an implant provides. Our look at wearable neurotechnology for focus and memory shows what this tier can and cannot realistically do today.
What implanted devices have achieved
The strongest evidence for invasive BCIs comes from people with paralysis who have used them to regain a function. In a 2012 study in Nature, Hochberg and colleagues showed two people with long-standing tetraplegia controlling a robotic arm to reach and grasp, using signals from a 96-channel microelectrode array in motor cortex. One participant, whose sensor had been in place for five years, used the arm to drink coffee from a bottle. The authors noted that the arm was not as fast or accurate as an able-bodied person’s.
Speech is the clearest recent example. In 2023, Willett and colleagues reported a speech-to-text BCI that recorded spiking activity from intracortical microelectrode arrays in a person with amyotrophic lateral sclerosis. It reached a 9.1% word error rate on a 50-word vocabulary and 23.8% on a 125,000-word vocabulary, decoding attempted speech at 62 words per minute. Natural conversation runs near 160 words per minute, so a gap remains, but earlier systems were far slower. A surface-electrode system from a different group reported a median of 78 words per minute at a 25% word error rate in the same year (Metzger et al.). As far as the studies cited here show, no non-invasive method has matched speech rates like these.
The middle path: devices inside blood vessels
Between open-brain surgery and a scalp cap sits a third option. In a first-in-human study published in 2020, Oxley and colleagues implanted a Stentrode, a mesh electrode delivered through the blood vessels, into the superior sagittal sinus next to the motor cortex, using a minimally invasive neurointervention procedure. Two participants with ALS learned to control mouse clicks with attempted movements, and both went on to use a computer for text messaging, online shopping and managing finances. Average click accuracy was about 93% for both, at roughly 14 and 20 correct characters per minute. That is slower than implanted arrays, and the sample was only two people, but the procedure avoided surgery on the skull. Our comparison of Neuralink, Synchron and Paradromics looks at how companies are pursuing these different designs.
What non-invasive systems can do
Scalp EEG has a long record of working for simple, repeatable tasks. In 1988, Farwell and Donchin described a speller based on the P300 response: a person watches a grid of letters flash and focuses on the one they want, and the computer detects the matching brain response. The approach still underlies many communication aids. It is slow and needs the user’s full attention, but it needs no surgery. For a closer look at what each recording method can and cannot measure, see our comparison of EEG, fMRI and ECoG.
Risks and open questions
Surgery carries the usual risks of any neurosurgical procedure, including infection and bleeding, and implanted hardware raises questions that take years to answer. Will the electrodes keep recording as scar tissue forms around them? Can a device be upgraded or removed safely? Who maintains it if the company behind it closes? The studies above followed small numbers of participants, so they show feasibility, not how common benefits or complications will be. Non-invasive systems avoid these risks, but their limits on signal quality mean they usually cannot offer the same level of control.
Which one is right?
It comes down to need. If the goal is restoring lost function for someone with a serious medical condition, the fidelity of an invasive implant justifies the surgery. If the goal is everyday focus, wellness, or research where safety and accessibility matter most, non-invasive is the obvious choice. The exciting middle ground, minimally invasive approaches like vein-threaded electrodes, is trying to capture some of the signal quality without full open-brain surgery, and it may end up being where much of the field lands.
Key takeaways
- Invasive BCIs give the clearest signal and the best results so far for speech and arm control, at the cost of surgery.
- Endovascular devices such as the Stentrode offer a middle path with a less invasive procedure, but early results come from very small studies.
- Non-invasive systems are safe and accessible, and work well for simple, repeatable tasks.
- Most published results involve a handful of participants, so they show what is possible, not what is typical.
Sources
- Hochberg et al., “Reach and grasp by people with tetraplegia using a neurally controlled robotic arm”, Nature, 2012.
- Willett et al., “A high-performance speech neuroprosthesis”, Nature, 2023.
- Metzger et al., “A high-performance neuroprosthesis for speech decoding and avatar control”, Nature, 2023.
- Oxley et al., “Motor neuroprosthesis implanted with neurointerventional surgery improves capacity for activities of daily living tasks in severe paralysis: first in-human experience”, Journal of NeuroInterventional Surgery, 2020.
- Farwell and Donchin, “Talking off the top of your head: toward a mental prosthesis utilizing event-related brain potentials”, Electroencephalography and Clinical Neurophysiology, 1988.
How we checked this: we compared the figures above with each paper’s published abstract and record. The studies are small, and some involved one or two participants.